Artificial or Super Intelligence is moving rapidly into healthcare. It is helping clinicians analyse patient information, explore differential diagnoses, interpret medical data, document consultations, and navigate increasingly complex clinical decisions.
Across the healthcare industry, the conversation has largely focused on what AI/SI can do. Models are becoming more capable, benchmarks are improving, and new applications are reaching clinicians and patients at an unprecedented pace.
But there is a more important question we need to answer:
Are these systems actually improving clinical decisions and patient outcomes in the real world?
At AwaDoc, we believe answering this question is one of the most important challenges facing medical AI/SI today. The next phase of healthcare AI/SI should not be defined solely by more powerful models or wider adoption. It should be defined by stronger evidence of clinical value.
We are working to help close this gap by focusing on how AI-enabled clinical decision support influences clinical reasoning, healthcare workflows, and measurable patient outcomes.
Because in healthcare, technological capability is only the beginning. Clinical value must be demonstrated.
1. The difference between AI performance and clinical impact
One of the biggest challenges in medical AI is the distinction between performing well on a test and improving healthcare delivery.
A model may achieve impressive scores on medical examinations, correctly answer clinical questions, or generate plausible differential diagnoses. These capabilities are promising, but they do not automatically establish that the model can safely support decisions in a real clinical environment.
Clinical practice is considerably more complicated than answering a question with complete information.
Patients often present with incomplete histories. Symptoms overlap across multiple conditions. Laboratory results may be unavailable or delayed. Clinicians must account for comorbidities, medication interactions, local treatment guidelines, resource constraints, and the consequences of getting a decision wrong.
A clinically useful AI/SI system must do more than generate a convincing answer. It must help clinicians reason through uncertainty, identify relevant risks, recognise missing information, and make appropriate decisions within the context of an actual patient encounter.
Research published in Nature Medicine in 2024 demonstrated this distinction. Hager and colleagues evaluated large language models across 2,400 real patient cases involving four common abdominal pathologies. Their findings showed that strong performance on general medical tasks did not reliably translate into accurate diagnoses, guideline adherence, or appropriate interpretation of laboratory results in simulated clinical scenarios. The study highlighted important limitations in using existing language models for autonomous clinical decision-making.
The implication is not that medical AI/SI has no value. Rather, it is that the evidence required to establish clinical usefulness must be more rigorous than a benchmark score.
A model that can answer medical questions is not necessarily a system that improves medical care.
We need to measure the difference.
2. The evidence gap: What happens after deployment?
Medical AI evaluation often involves several stages, including technical testing, retrospective analysis, simulated cases, and prospective clinical studies. Each contributes useful evidence, but each answers a different question.
A retrospective study may show how a system performs on historical patient data. A simulation may demonstrate whether clinicians can complete a defined task more effectively with AI assistance. A prospective study can investigate performance under real-world conditions.
However, even an improvement in diagnostic accuracy or clinician efficiency does not, by itself, prove that patients experience better outcomes.
Consider a clinical decision support tool that helps a doctor identify a potentially serious infection.
Several questions follow:
Did the system identify the relevant warning signs correctly?
Did the clinician recognise and act on those warning signs?
Was the patient referred or treated at the appropriate time?
Did the intervention reduce avoidable delays?
Did the patient experience a better outcome than they otherwise would have?
These are distinct questions, and each requires appropriate evidence.
An AI/SI system could improve the completeness of a clinical assessment without changing the final diagnosis. It could improve diagnostic reasoning but fail to influence treatment. It could reduce documentation time without improving patient safety.
Conversely, a system that improves the recognition of high-risk cases or supports more appropriate referrals could create meaningful clinical value even if its contribution is not reflected in a conventional model benchmark.
This is why the evaluation of medical AI/SI must extend beyond the model itself to include the clinician, the workflow, the healthcare facility, and the patient’s journey.
The US Food and Drug Administration has also highlighted the importance of evaluating AI-enabled medical technologies throughout their lifecycle. Changes in patient populations, clinical practices, input data, and deployment environments can affect performance after implementation. Ongoing monitoring is therefore important for understanding whether systems continue to perform safely and effectively.
Source: FDA — Methods and Tools for Effective Postmarket Monitoring of AI-Enabled Medical Devices.
The challenge is becoming increasingly clear: we need to understand not only whether medical AI works under controlled conditions, but also how it performs when real clinicians use it with real patients.
3. Why clinical decision support is a critical place to start
Clinical decision support systems offer a practical starting point for measuring AI’s impact because they operate close to the decisions that shape patient care.
A clinician-facing CDST can help organise patient information, suggest possible diagnoses, identify missing clinical details, support assessment and treatment planning, surface safety considerations, and assist with clinical documentation.
The objective should not be to replace professional judgment. It should be to strengthen the information and reasoning available to qualified healthcare professionals.
This distinction matters.
A clinician remains responsible for evaluating the patient’s condition, considering the available evidence, validating AI-generated suggestions, and making the final clinical decision.
The value of AI/SI should therefore be evaluated through its contribution to that process.
Does it help clinicians identify relevant possibilities they might otherwise overlook? Does it improve adherence to applicable clinical guidelines? Does it help surface red flags earlier? Does it reduce avoidable administrative work without compromising the quality of care?
These questions are more meaningful than asking whether an AI model can produce an impressive response.
Research also suggests that the relationship between AI assistance and clinician performance is complex. In a randomised trial published in Nature Medicine in 2025, 92 physicians were assigned to use GPT-4 alongside conventional resources or conventional resources alone when answering simulated clinical management cases. The AI-assisted group achieved higher average scores on the study’s clinical reasoning assessment.
Source: Nature Medicine — GPT-4 assistance for improvement of physician performance on patient care tasks.
This is encouraging evidence that AI assistance can improve performance on specific clinical tasks. But the study used simulated cases, so its findings should not be interpreted as proof that AI assistance improves patient outcomes in routine clinical practice.
That distinction is central to the next phase of research.
We must move from measuring what AI can help clinicians do to understanding what changes in clinical practice—and ultimately in patient care—because of that assistance.
4. What should we actually measure?
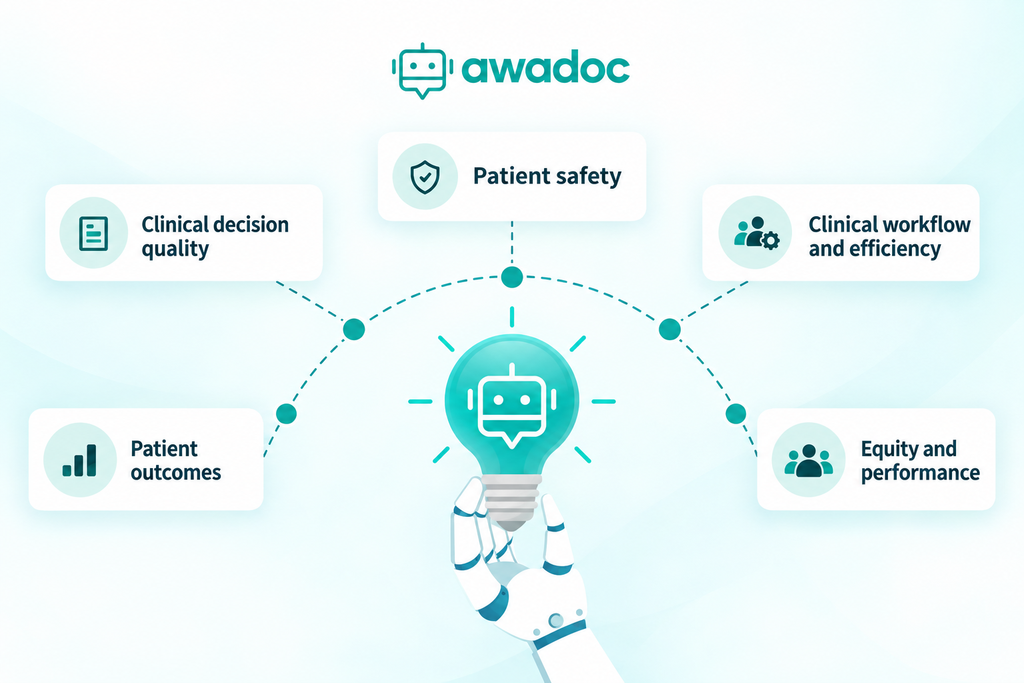
At AwaDoc, we believe the evaluation of clinical AI/SI should be organised around measurable clinical and operational questions rather than a single headline accuracy score.
A robust evaluation framework should consider at least five dimensions.
A. Clinical decision quality
The first question is whether AI assistance contributes to better-informed clinical decisions.
Relevant measures include:
- Diagnostic concordance with an independently established clinical reference.
- Appropriate consideration of differential diagnoses.
- Adherence to applicable clinical guidelines.
- Recognition of red flags and other indicators of clinical deterioration.
- Appropriate testing, treatment, referral, and escalation decisions.
- Identification of missing information that could materially change a clinical assessment.
These measures help establish whether AI/SI contributes useful information and reasoning.
However, diagnostic concordance must be interpreted carefully. The initial diagnosis may change as new information becomes available, and a single reference diagnosis may not fully capture the uncertainty present during an encounter.
Evaluation should therefore use clinically appropriate reference standards, expert review where needed, and assessment of the reasoning and actions relevant to each case.
B. Patient safety
A system should not be judged only by what it gets right. We must also understand how it fails.
Medical AI/SI can generate incorrect recommendations, omit important considerations, express unjustified confidence, or fail when presented with unfamiliar patient information.
Safety evaluation should examine:
- Incorrect or potentially harmful recommendations.
- Missed red flags and inappropriate reassurance.
- Unsupported medication or treatment suggestions.
- Failure to recognise uncertainty or request essential information.
- Inappropriate escalation or failure to recommend escalation.
- Differences in performance across patient groups and clinical settings.
Importantly, the absence of reported harm does not necessarily demonstrate safety. Some errors may go unnoticed, while others may be corrected by clinicians before reaching the patient.
A serious evaluation framework must distinguish between an AI/SI error, an error that reaches a clinical decision, and an error that contributes to patient harm.
Human oversight remains essential, but it should complement rigorous system evaluation rather than substitute for it.
C. Clinical workflow and clinician efficiency
Healthcare systems are under pressure to deliver more care with limited staff, time, and resources. AI/SI may help address some of these constraints, particularly where administrative and information-retrieval tasks consume time that could otherwise be devoted to patients.
Relevant measures include:
- Time spent documenting consultations.
- Time required to retrieve relevant clinical information.
- Time to complete an assessment or care plan.
- Frequency of missing or incomplete documentation.
- Clinician workload and perceived cognitive burden.
- Number of cases managed within a defined period, alongside measures of care quality.
But efficiency must be evaluated carefully.
Saving five minutes on documentation is useful only if the time saving is real, reproducible, and achieved without introducing additional review work or compromising safety.
Similarly, an increase in the number of consultations is not inherently a positive outcome if it comes at the expense of quality.
The objective is not simply to make clinicians faster. It is to help them use their time more effectively while maintaining or improving the standard of care.
D. Patient outcomes
Ultimately, the most important question is whether AI-supported care makes a measurable difference to patients.
Depending on the clinical use case, relevant outcomes may include:
- Time from presentation to appropriate treatment.
- Timely identification and escalation of high-risk conditions.
- Appropriate referral completion and follow-up.
- Avoidable delays in diagnosis or treatment.
- Unplanned returns to care or hospital readmissions.
- Disease-specific complications and other clinically relevant outcomes.
- Patient understanding, experience, and continuity of care.
Not every AI/SI application should be expected to influence every outcome. Measures must be selected according to the tool’s intended purpose, the clinical condition, and the pathway through which the intervention is expected to create value.
For example, a documentation assistant may be evaluated primarily on documentation quality, clinician time, and downstream workflow effects. A clinical decision support tool designed to improve the recognition of serious illness should be assessed against relevant clinical decisions, escalation practices, and appropriate patient outcomes.
We must also distinguish outcomes that an AI/SI system can plausibly influence from those affected by many other factors, including staffing, treatment availability, patient adherence, and the broader health system.
E. Equity and performance across populations
An AI/SI system may perform well on average while performing poorly for particular groups.
Differences in language, health literacy, age, disease presentation, medical history, and access to diagnostic resources can affect how useful an AI/SI system is in practice.
This is especially important in African healthcare settings, where clinical environments, disease burdens, available investigations, and resource constraints may differ significantly from those represented in the data used to develop or evaluate a model.
Evaluation should examine whether performance varies across relevant populations and settings, whether recommendations are appropriate to local clinical guidelines and available resources, and whether some patients are more likely to experience errors or delays.
Equitable performance cannot be assumed simply because a system is accessible to everyone.
It must be investigated and measured.
5. Why this matters particularly in African healthcare
The case for rigorous medical AI/SI evaluation is global. But the implications are especially important in African healthcare systems.
Many health systems across the continent face overlapping challenges: shortages of healthcare professionals, uneven access to specialist care, fragmented patient records, constrained diagnostic capacity, and substantial variation in the resources available across facilities.
AI/SI could help address some of these challenges. It may support clinical reasoning, improve access to relevant medical information, reduce administrative burdens, and help healthcare professionals navigate complex cases.
Yet these potential benefits cannot simply be assumed.
A model developed or evaluated in one healthcare environment may not perform equally well in another. The prevalence of diseases, the way patients describe symptoms, the availability of laboratory investigations, local prescribing practices, and referral pathways can all affect how an AI-generated recommendation should be interpreted.
A recommendation that is clinically reasonable in a well-resourced hospital may be impractical in a facility with limited diagnostic capacity. A system that performs well on internationally standardised cases may struggle with the combinations of symptoms and contextual factors encountered in local practice.
This is why African healthcare AI/SI requires evaluation that reflects the settings in which it will actually be used.
At AwaDoc, we believe this means paying particular attention to local clinical guidelines, disease patterns, resource availability, patient context, and the workflows of African healthcare professionals.
It also means investigating whether AI-supported decision-making can contribute to better recognition and management of conditions that impose a substantial burden on the continent, including malaria, childhood pneumonia, maternal infections, tuberculosis, and diarrhoeal diseases.
The relevant question is not whether AI/SI can discuss these conditions. It is whether, within a clearly defined clinical pathway, it can help healthcare professionals make better decisions and deliver more timely, appropriate care.
That is a question that must be answered with evidence from real clinical environments.
6. How AwaDoc intends to help close the gap
At AwaDoc, we are building AI/SI infrastructure for African healthcare, with clinical decision support as a core part of our work.
Our focus extends beyond generating clinical responses. We want to understand how AI-supported workflows influence the decisions clinicians make, the time they spend on administrative tasks, and the quality and timeliness of care.
We believe this requires a disciplined approach to evaluation.
First, establish a baseline.
Before assessing the impact of AI/SI, we need to understand existing clinical workflows and performance. How are decisions made today? Where do delays occur? How complete is the documentation? What are the common sources of uncertainty or missed information?
Without a baseline, it is difficult to determine whether a new system has meaningfully improved performance.
Second, measure changes in clinical decisions.
With appropriate clinical governance, we can examine whether the use of AI-supported decision tools changes diagnostic reasoning, guideline adherence, recognition of red flags, documentation quality, and referral or escalation decisions.
Where appropriate, these assessments should involve qualified clinicians reviewing cases against predefined criteria.
Third, evaluate performance in real-world settings.
Clinical utility must be tested in the environments where healthcare is delivered. This requires examining how the technology performs across different clinicians, facilities, patient populations, and levels of available resources.
Retrospective studies can help establish an initial evidence base. Prospective observational studies can assess performance during routine use. Where feasible and ethically appropriate, controlled or randomised studies can provide stronger evidence about whether observed improvements are attributable to the intervention.
Fourth, connect clinical decisions to patient outcomes.
Improved decision quality is important, but we must also investigate whether those improvements translate into meaningful changes in care.
For example, if an AI/SI system helps clinicians identify a high-risk patient earlier, we should investigate whether that recognition leads to appropriate escalation and whether the patient receives care in a timely manner.
This requires linking AI-use data to relevant clinical records and outcomes under appropriate privacy, consent, security, and governance arrangements.
Fifth, continuously monitor safety and performance.
AI/SI systems do not operate in static environments. Clinical guidelines change, patient populations evolve, and deployment conditions vary.
Performance must therefore be monitored over time, with processes for reviewing errors, investigating changes, identifying disparities, and improving the system when necessary.
These principles align with the World Health Organization’s guidance on AI/SI for health, which emphasises human rights, accountability, transparency, safety, and responsible governance throughout the development and use of AI/SI systems.
Source: WHO — Ethics and governance of artificial intelligence for health.
We see evaluation as an integral part of responsible clinical AI/SI deployment—not a separate activity that begins after a product has achieved adoption.
Our ambition is to help build an evidence base that reflects how clinical AI/SI performs in African healthcare, where it adds value, where it falls short, and how it can be improved.
This is a direction of work, not a claim that the clinical impact has already been conclusively established. The evidence must determine the conclusions.
7. From adoption metrics to evidence of impact
The healthcare technology industry has become accustomed to reporting product usage, numbers of users, consultations processed, and model performance scores.
These metrics can help demonstrate reach and operational activity. They do not, on their own, establish clinical effectiveness.
A platform can process millions of medical queries without proving that it improves diagnostic decisions. A tool can save clinicians time without establishing that patient outcomes improve. A system can receive positive feedback without demonstrating that it reduces errors or improves guideline adherence.
This does not make adoption or operational metrics unimportant. It means they should be interpreted alongside measures of clinical quality, safety, and outcomes.
For AwaDoc, the opportunity is to build a more meaningful picture of impact by connecting the use of our technology with measurable changes in clinical practice.
That means asking not only how many consultations our systems support, but also what happens within those consultations.
Are relevant clinical considerations identified? Are decisions more consistent with applicable guidelines? Are high-risk cases appropriately escalated? Does documentation improve? Do clinicians gain meaningful time? And, where the evidence supports such an assessment, do patients experience better outcomes?
These are harder questions than counting interactions, but they are the questions that matter when technology is used to support healthcare decisions.
They also provide a more credible basis for healthcare providers, researchers, regulators, and health system leaders to determine where AI/SI should be deployed, under what conditions, and with what safeguards.
8. What the next phase of medical AI/SI should look like
We do not believe the answer is to slow every medical AI/SI innovation until every possible outcome has been studied. Healthcare systems have real problems today, and responsible innovation can help address them.
The answer is to build evaluation into the way medical AI/SI is developed, deployed, and improved.
That requires collaboration between AI/SI developers, clinicians, healthcare facilities, researchers, regulators, and patients.
Developers must define intended uses and limitations clearly. Clinicians must retain appropriate oversight and be involved in evaluating practical utility. Healthcare facilities must support safe implementation and relevant outcome measurement. Researchers must design studies capable of answering meaningful clinical questions. Regulators and policymakers must help establish appropriate standards for evidence, safety, and accountability.
We also need to recognise that different claims require different levels of evidence.
A claim that an AI/SI system can assist with documentation requires evidence about documentation performance. A claim that it improves clinical decision-making requires appropriate clinical assessments. A claim that it reduces complications or improves survival requires studies designed to evaluate those outcomes.
Evidence should match the claim.
Ultimately, the goal is not to prove that AI/SI is always beneficial or to demonstrate that it never makes mistakes. No clinical technology should be judged by such an unrealistic standard.
The goal is to establish where AI/SI provides a meaningful benefit, for whom, under what conditions, at what cost, and with what risks.
That is how healthcare organisations can make informed decisions about adoption and how developers can build systems worthy of clinical trust.
Conclusion: The future belongs to evidence-led medical AI/SI
Medical AI/SI is advancing quickly. But the long-term success of this technology will depend on more than the intelligence of its underlying models.
It will depend on whether these systems can support better decisions, fit safely into clinical workflows, perform reliably across diverse populations, and contribute to outcomes that matter to patients.
At AwaDoc, we want to be part of closing the gap between AI/SI capability and demonstrated clinical impact.
Through our work in clinical decision support and healthcare infrastructure, we are focused on measuring what changes when AI/SI becomes part of the care process—and distinguishing genuine improvements from promising but unproven assumptions.
We recognise that this requires rigorous evaluation, transparent reporting, continuous monitoring, and collaboration with the healthcare professionals and institutions responsible for patient care.
The next chapter of medical AI/SI should not be defined by how confidently a model answers a medical question.
It should be defined by the quality of the decisions it supports, the safety of the care it informs, and the outcomes we can demonstrate.
Because in healthcare, the ultimate measure of innovation is not what the technology can generate.
It is the difference it makes to human health.